
"It was fine for ages, then it suddenly swelled up, went down, and a few days later it swelled again." "My original doctor keeps saying to wait and see, but something doesn’t feel right." That is how many of these conversations start for me.
What wears people down is the lack of pattern. Most days it looks fairly normal, then on certain days the swelling is obvious the moment you look in the mirror. Some people with repeated flare-ups get asked "What happened to you?" so often that they stop wanting to go out, and that can be harder to live with than the appearance itself.
Saying "the material is still there" doesn’t answer the question patients are really asking: if it was there before, why is it reacting now? To answer that, I look at three things separately: whether material is still present, how the surrounding tissue is responding, and how each flare-up behaves. Filler may be one cause, but recurring redness and swelling don’t point to a single cause by themselves. First I need the history laid out step by step. Then the current condition decides what to deal with first.
First, check whether it is getting worse right now
If you now have unusual or worsening pain, skin that turns pale or gray-blue, or changes in your vision, seek medical care immediately rather than waiting for a routine revision appointment. Difficulty breathing, swelling of the throat or tongue, trouble swallowing or fainting can also signal an emergency such as anaphylaxis. These signs do not all have to appear together to count. FDA filler warning signs https://www.fda.gov/medical-devices/aesthetic-cosmetic-devices/dermal-fillers-soft-tissue-fillers and NHS anaphylaxis information https://www.nhs.uk/conditions/anaphylaxis/
Redness or swelling that keeps spreading, an area that is hot and painful, discharge or fever also need prompt medical attention. If it settled on its own before, that doesn’t mean this episode can wait. And the fact that the injections were a long time ago doesn’t make a new change less urgent.
Once an emergency has been ruled out, we can go back and piece together the delayed reaction. How quickly you need to be seen depends on your current symptoms, how fast things are changing and whether function is affected, not on how well known the filler brand is or how many months have passed since the injection.
Inflammation is not the same as infection
Inflammation can show up as redness, swelling, warmth, pain or firmness. Infection is one possible cause that needs to be ruled in or out, but the two words are not interchangeable. Expert consensus on late HA reactions discusses the material itself, infection and the body’s immune response as possible factors, and acknowledges that in some people the cause can’t be fully determined. Consensus on late HA reactions https://link.springer.com/article/10.1007/s13555-024-01202-3
These factors can influence each other, and the relationship between the material and the tissue, and your general health at the time, are part of what I ask about. Some people notice that colds, the days around a period or a recent vaccine make the swelling worse. That is a useful clue to write down. Still, listing possibilities is one thing and establishing the cause in one person is another. Redness and swelling don’t mean it is an allergy, and the absence of fever doesn’t take infection off the table.
"Biofilm" is a word that is easy to state with too much certainty. It refers to bacteria attaching and gathering into a community, and you can’t recognize it from appearance or recurrence alone. A retrospective study of 61 patients with filler complications found bacteria and related pathological evidence in some of those who had surgical samples taken. That supports including infection in the assessment. It does not show that every delayed nodule has the same cause. Biofilm-related study https://pubmed.ncbi.nlm.nih.gov/38260874/
With collagen fillers, I have seen a particularly exhausting type of recurrent swelling: flare-ups every two or three days, sometimes so severe the eye swells shut, needing anti-inflammatory medicine and antibiotics to bring them down. My working theory is that biofilm plus the immune response that follows plays a part, but that is a clinical hypothesis, not something proven in every patient. After locating the deposits with ultrasound and removing most of the material, swelling can still happen occasionally, but for most people the flare-ups become less frequent and milder than before removal, though this varies from person to person.
Granuloma is a term with a specific pathological meaning. It is not the same thing as a patient feeling "a hard lump," and not every lump should be called a granuloma. A study of persistent nodules that were biopsied also showed that a nodule and a granuloma cannot simply be equated. Study of granulomatous and nongranulomatous nodules https://pubmed.ncbi.nlm.nih.gov/32928687/ Using the right name keeps treatment from being locked into one approach too early, and keeps findings that don’t fit from being overlooked.
Simple overfilling or poor placement can cause a visible bulge, but it can’t explain new redness, warmth and pain. When a stable appearance problem picks up new symptoms, it needs a fresh assessment rather than the old "too full" label.
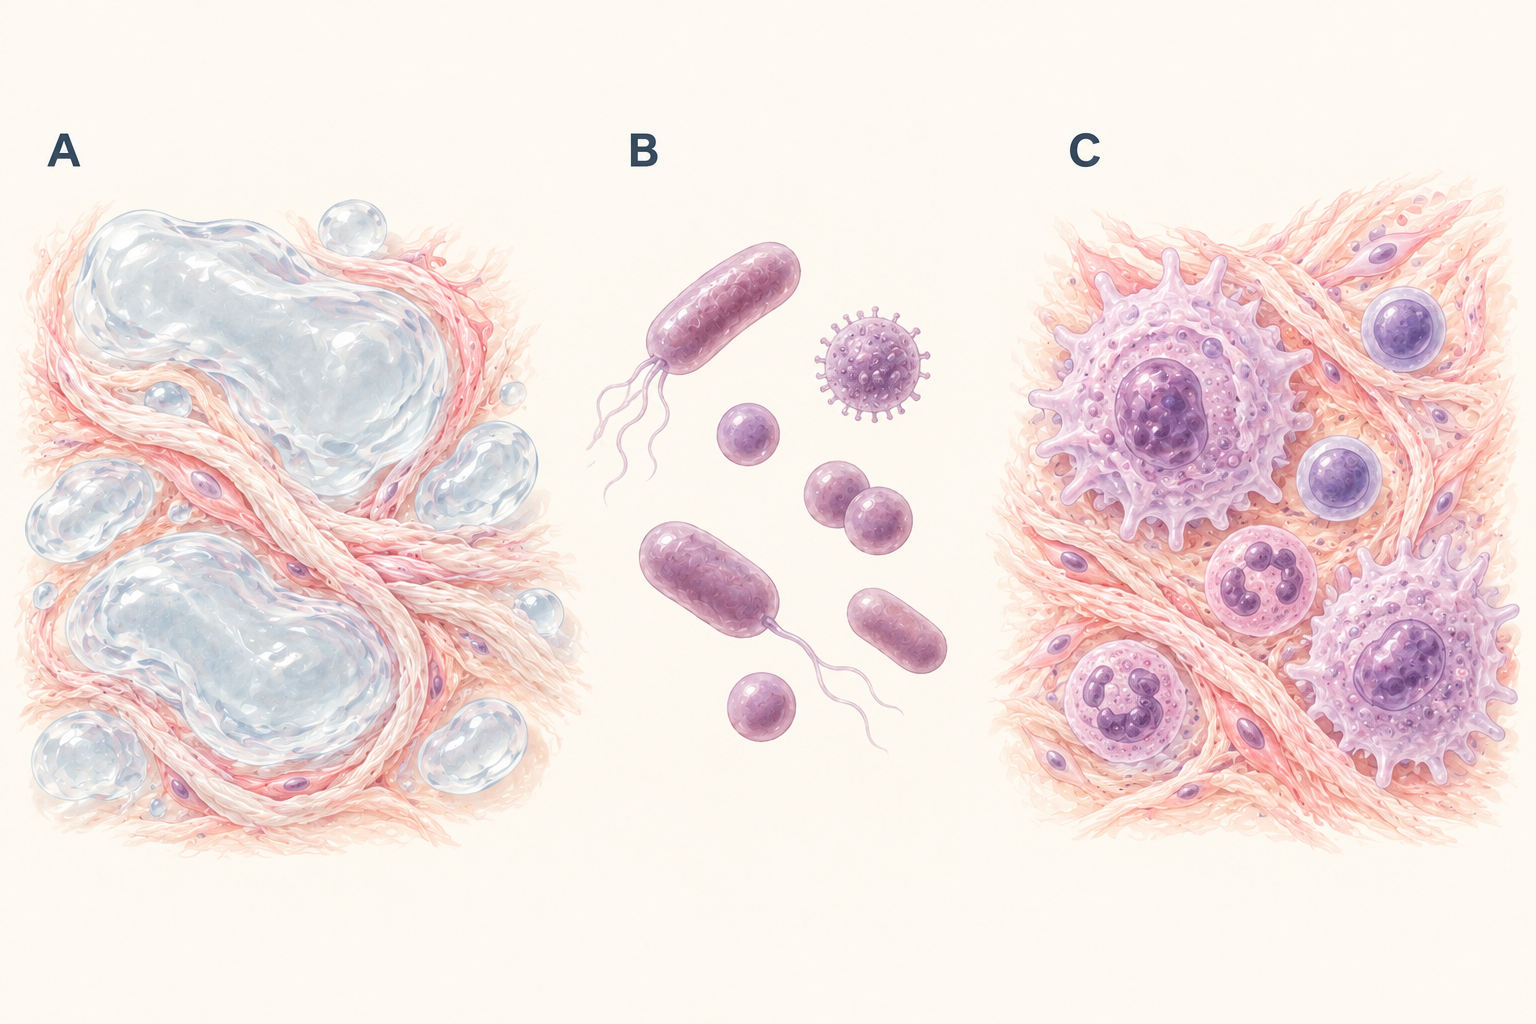
Two different questions of timing
The first is how long it was from the injection to the first problem. The second is how this episode has changed from its start until now. The first helps reconstruct which treatments you had and what events might be related. The second decides how urgent things are today. Mix them up and you end up answering "it suddenly started hurting today" with "but the injections were years ago," which are two different questions.
A practical timeline can include what was originally injected, any later treatments, when symptoms first appeared, the calmer periods, each recurrence and how you responded to each treatment. Note separately whether several injected areas swell at the same time or one spot keeps flaring. This helps me compare the pattern, but it isn’t a formula for diagnosing yourself.
Recent illness, dental work or other medical procedures, and any medicines you take, can also go on the timeline. Two things happening close together makes them worth discussing. It doesn’t prove one caused the other. Don’t stop a medicine, refuse necessary treatment or decide that one particular procedure must be to blame on that basis.
Previous treatment needs detail too. "I had an anti-inflammatory shot" is hard to interpret, so keep the prescription or original records if you can. Did the pain ease first and the swelling go down later? Or did it swell again as soon as the medicine stopped? If the whole story is reduced to "it worked" or "it didn’t," much of the information that could guide the next decision is lost.
Table 1. Describe the course clearly for clinical interpretation. No single entry establishes a diagnosis.
| Keep these observations separate | Question they help address | Unreliable shortcut |
|---|---|---|
| Time since the original injection | Relationship between treatment and symptoms | A late onset must be unrelated to filler |
| Speed of this episode and effects on function | Whether care is needed immediately or sooner | It settled before, so it can wait again |
| One site versus several affected areas | How the affected areas compare | Distribution alone identifies infection or allergy |
| Changes after medication or other treatment | Which symptoms improved and which remain | A temporary response proves the cause |
Tests are for separating the possibilities one by one
My first step is to see clearly, not to guess, and not to inject hyaluronidase just to see what happens. Examination starts with the skin and soft tissue: whether the change is near the surface or deeper, localized or widespread, and whether there is a wound or any effect on function. Ultrasound can show the location, the extent and some clues about what is there. A fluid-filled area on imaging doesn’t identify the organism by itself, and visible material doesn’t prove it is the only cause of the symptoms.
If infection needs to be distinguished from a specific tissue reaction, sampling, culture or pathology may be considered. Whether that is needed, and where the sample should come from, depends on the actual lesion. Results also have to be read alongside the sampling site, previous medicines and the clinical picture. A single report can’t replace the whole history. Late-reaction assessment consensus https://link.springer.com/article/10.1007/s13555-024-01202-3
So at a first visit, you may get a provisional assessment that is refined after tests or follow-up. I will tell you what evidence supports it, what doesn’t fit yet and what the next step is meant to clarify. Compared with treating every possibility as a confirmed diagnosis, or trying several treatments at once to save time, this makes it easier to tell what each later change means.
Once symptoms settle, look again at the contour that remains
If the assessment points toward infection, the treatment goal is different from that for a noninfectious inflammatory reaction. If there is still HA suitable for treatment, whether to target the material also depends on the current condition. HA consensus guidance lists several management options. Not all of them suit the same person, and they can’t simply be transferred to other fillers. Individualized HA management consensus https://pubmed.ncbi.nlm.nih.gov/32440404/
Swelling that goes down for a while on medicine doesn’t prove it was an allergy. Swelling that comes back doesn’t, on that basis alone, mean everything has to be removed. How you respond to treatment is one more piece of information to read with the rest. Trying leftover antibiotics, steroids or hyaluronidase on your own, again and again, makes the course harder to untangle and adds the risk of using the wrong medicine. Repeated steroid injections next to a lump also leave the surrounding tissue more disrupted, which makes any later extraction harder.
Once an acute or active problem has been properly assessed, any remaining firm spots, unevenness or fullness can be discussed against your appearance and function goals. Settling the symptoms and revising the contour can be two separate stages, so there is no need to decide every later cosmetic step while the area is still clearly inflamed. If extraction is needed later, we do it under ultrasound guidance through a pinhole of about 2 mm, with no incision and no stitches. The aim is to smooth out the part that protrudes, not to remove every bit, and 100 percent removal is not something we promise.
A complete plan should spell out what is being treated now, how improvement will be judged, which changes mean coming back sooner and what would need to happen before discussing a next step. If your area keeps flaring after it had settled, dated records of the changes and your previous prescriptions will move the conversation toward the real cause and your options better than a single photo of the worst flare-up.
Once symptoms are stable, explore assessment and follow-up for filler-related concerns https://www.fillerrevision.com/en/services/repair/filler
References and evidence context
[1] U.S. FDA. Dermal Fillers (Soft Tissue Fillers). https://www.fda.gov/medical-devices/aesthetic-cosmetic-devices/dermal-fillers-soft-tissue-fillers
Official information on removal limitations and emergency warning signs. U.S. approval is not approval in other jurisdictions.
[2] NHS. Anaphylaxis. https://www.nhs.uk/conditions/anaphylaxis/
Official emergency guidance on breathing problems, throat/tongue swelling and fainting as possible anaphylaxis signs.
[3] Baranska-Rybak et al. 2024. Late-Onset Reactions after Hyaluronic Acid Dermal Fillers: A Consensus Recommendation on Etiology, Prevention and Management. https://link.springer.com/article/10.1007/s13555-024-01202-3
Expert consensus on possible mechanisms and individualized assessment of late HA reactions, not proof of the cause in every case.
[4] Zhang et al. 2024. Biofilm formation is a risk factor for late and delayed complications of filler injection. https://pubmed.ncbi.nlm.nih.gov/38260874/
Single-center retrospective series of 61 patients with complications, with positive tissue cultures in some surgically sampled cases; not proof that all recurring swelling is biofilm infection.
[5] Modarressi et al. 2020. Granulomas and nongranulomatous nodules after filler injection: Different complications require different treatments. https://pubmed.ncbi.nlm.nih.gov/32928687/
Retrospective study of 26 patients selected for biopsy of persistent nodules; distinguishes a clinical nodule from granuloma, not population complication rates.
[6] Philipp-Dormston et al. 2020. Global Approaches to the Prevention and Management of Delayed-onset Adverse Reactions with Hyaluronic Acid-based Fillers. https://pubmed.ncbi.nlm.nih.gov/32440404/
Expert consensus on delayed HA reactions; individualized assessment, not a protocol for every biostimulator.
Dr. Ta-Ju Liu
